
The Surgeon Said “Clean Margins.” The Cancer Didn’t Get the Memo.
Why “tumor constitution” explains less than it sounds like, how MRD testing changes the postoperative conversation, and why DC vaccines are not the sure thing the internet makes them sound.
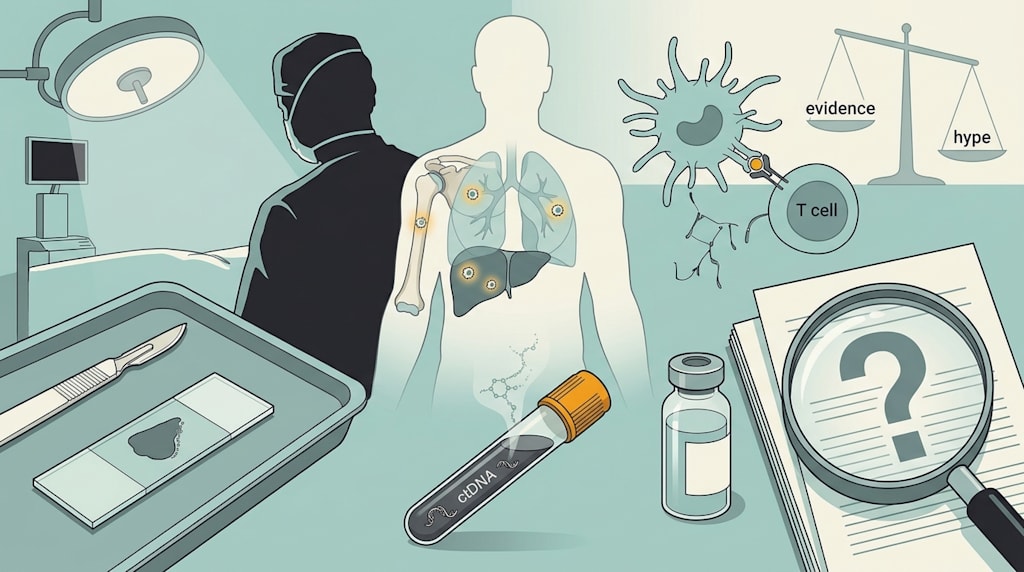
“The surgery was very successful.” Cancer patients want to hear that sentence. They also tend to misread it.
When a surgeon says “successful,” the meaning is concrete: the visible lesion was completely removed, the margins were negative, and the lymph node dissection was adequate. In that sense, the surgery really was successful. Biological cure is a different claim. A patient whose pathology report says “negative margins” may still carry millions of tumor cells that no scan can see. Those cells sit in the bone marrow, the liver, or the lung microenvironment and wait for a gap in immune surveillance.
This is the center of the postoperative recurrence problem. Surgery removes what imaging can see. It cannot remove what imaging cannot see. The result is an unequal contest between the limits of surgical boundaries and the persistence of tumor biology. Around that contest, two stories have become popular. One is “tumor constitution.” The other is the DC vaccine breakthrough. Both sound coherent. Both need a closer look.
“Tumor constitution”: a phrase that explains everything and therefore explains nothing
“Tumor constitution” is attractive because it gives recurrence a simple causal picture. The body’s “soil” was already friendly to cancer. Surgery pulled the weeds. The soil stayed the same. The weeds grow back.
That picture merges two different things. The first is immune evasion by tumor cells. Tumor cells downregulate antigen presentation, recruit immunosuppressive cells, and build an immunosuppressive microenvironment. This is a biological process with molecular mechanisms that can be observed and targeted. The second is “constitution,” a pre-scientific description that does not separate causal levels, does not generate testable predictions, and does not point to a specific intervention.
The causal direction is also reversed. An “incompetent immune system” did not simply cause the tumor. The tumor itself weakens and trains the immune system. A 2025 review in International Journal of Molecular Sciences on minimal residual disease in breast cancer stated that recurrence depends on the balance between the immunosuppressive tumor microenvironment and antitumor immune responses. Removing the primary lesion reduces that immunosuppressive weight. It does not erase it. Surgery and perioperative stress also cause temporary immunosuppression, which creates a vulnerable window.
The immune problem after surgery is therefore a specific risk that can be defined and monitored at the molecular level. It is not a vague state to be repaired through “constitution regulation.” The harm in the “tumor constitution” label is not that it is entirely wrong. The harm is that it pulls attention away from risk assessment and evidence-based treatment and redirects it toward something that cannot be verified.
MRD: making the invisible residual disease visible
If “tumor constitution” is a black box, minimal residual disease is the key that opens it.
MRD refers to tumor cells or tumor-derived DNA that remain after curative treatment and cannot be detected by routine imaging or protein markers. Circulating tumor DNA is the most clinically feasible MRD test today. Tumor cells release ctDNA into the blood. Ultra-deep sequencing or methylation detection can catch a molecular recurrence signal months before imaging finds a lesion.
The data are concrete. A 2025 longitudinal ctDNA study in lung cancer published in Cell found that patients who were ctDNA-positive at the postoperative landmark point, between 10 and 120 days after surgery, had a positive predictive value of 86.2%. Nearly nine in ten patients with detectable ctDNA eventually recurred. Specificity was 92.5%. In pancreatic cancer, postoperative ctDNA positivity has been described as the strongest recurrence predictor, independent of clinicopathological factors, and it can signal recurrence about five months before imaging confirmation. In breast and lung cancers, ctDNA-MRD testing moved the median warning time to 112 days and 83 days, respectively. A meta-analysis of eight studies and 423 patients with gastric cancer put the pooled hazard ratio for recurrence at 6.37 for postoperative ctDNA positivity. At the postoperative time point, the figure rose to 14.09.
These numbers do not predict fate. They change the starting point of postoperative management. The traditional model infers risk from stage, lymph node status, and margin status. That is a probability judgment based on group averages. ctDNA-MRD gives individual, changing molecular evidence. A patient with stage II colon cancer whose postoperative ctDNA stays negative may have a low enough risk to discuss omitting or simplifying adjuvant chemotherapy. A patient who looks “early-stage” but is ctDNA-positive needs to be treated as high-risk and entered into closer surveillance or a clinical trial.
MRD testing is not perfect. ctDNA release varies by tumor type. Detection platforms have not been standardized for sensitivity and specificity. Early postoperative sampling, within 48 to 72 hours, can produce false positives from tumor DNA released during surgery. These are problems of technical maturity, not conceptual validity. “Tumor constitution” cannot produce a falsifiable prediction. MRD at least puts the problem on a track that can be measured, tested, and improved.
DC vaccines: the gap between the Nobel halo and the clinical evidence
DC tumor vaccines are the most emotionally persuasive alternative in the postoperative recurrence conversation. The narrative goes like this. Dendritic cells are the commanders of the immune system. The 2011 Nobel Prize in Physiology or Medicine went to Ralph Steinman for discovering DCs. Load a patient’s DCs with tumor antigens, reinfuse them, and the immune system learns to find and kill residual tumor cells. The logic feels airtight.
Logical coherence is not clinical efficacy. Immunological plausibility is only an entry ticket. Survival benefit requires randomized controlled trials. On that measure, DC vaccines have a weaker record than the narrative suggests.
The “FDA approval” cited in popular accounts refers to Sipuleucel-T, or Provenge. It was approved in 2010 for asymptomatic or minimally symptomatic metastatic castration-resistant prostate cancer. It was not approved for postoperative recurrence prevention. The pivotal phase III IMPACT trial reported median overall survival of 25.8 months versus 21.7 months, a gain of 4.1 months, with a 22% relative reduction in risk of death. That is a statistically significant benefit. It is also a benefit measured in months, in an advanced population with a median survival under two years. Extrapolating it to “DC vaccines prevent recurrence across solid tumors” crosses two steps that should not be crossed: from advanced treatment to postoperative adjuvant prevention, and from one tumor type to many. The real-world PROCEED registry reported a median OS of 30.7 months in nearly two thousand patients. The direction matched the trial. The size of the benefit did not change the overall picture.
In glioblastoma, the most discussed DC vaccine case, DCVax-L needs a methodological microscope. A systematic review reported median OS of 19.3 months versus 16.5 months against external controls, with 5-year survival of 13.0% versus 5.7%. The numbers are not trivial. The key phrase is “external controls.” The most cited positive study did not use a concurrent randomized control group. It compared vaccinated patients with historical data or patients from other trials. The same review concluded that the evidence quality was low because of trial design limits and two negative randomized trials. As of 2025, DCVax-L has not received FDA approval. Some reviews still call it experimental. A marginal benefit in one tumor type, derived from external controls and rated low-quality evidence, cannot support the claim that DC vaccines are a new breakthrough in postoperative recurrence prevention.
In melanoma, the evidence points more directly negative. The 2025 ABSIDE phase II randomized trial found that DC vaccination in advanced melanoma was safe and immunogenic, but it found no evidence of improved clinical outcomes. Immune activation and clinical benefit often separate in cancer immunotherapy. Antigen-specific T cells in peripheral blood do not necessarily break through the tumor microenvironment, infiltrate residual lesions, and kill tumor cells. Equating immunogenicity with efficacy is the most common logical leap in the DC vaccine story.
The “extend the short peptide” strategy mentioned in popular articles points to a reasonable technical direction: improve the durability and strength of antigen presentation. The existence of that direction shows that the field has not solved its core efficacy problem. It does not show that the problem is solved. In pancreatic cancer, as of 2025, no completed phase III randomized controlled trial has reported DC vaccine results. Even the basic question of survival benefit has no level I evidence in that tumor type.
A practical framework for postoperative recurrence prevention
Criticism of DC vaccines is not a rejection of immunotherapy. The immune system does play a real role in controlling MRD. That is exactly why specific therapies need strict evidence standards. A vaccine that failed to improve clinical outcomes in a phase II trial should not receive clinical status it has not earned because its immunological backstory is elegant.
Based on current evidence, a more reliable framework for postoperative recurrence prevention rests on risk stratification and proven intervention.
First, use MRD to redefine risk instead of blurring risk with “constitution.” Postoperative ctDNA testing can turn “will it come back?” into a specific clinical decision. Patients who are MRD-negative and stay negative may be spared unnecessary adjuvant treatment. Patients who are MRD-positive need to be identified as candidates for additional intervention. Prospective phase III trials of ctDNA-guided adjuvant treatment are still running. Whether they improve survival is not yet known. At least the path can be tested.
Second, keep proven adjuvant therapy. For patients with indications, standard adjuvant chemotherapy, targeted therapy, or endocrine therapy has randomized trial evidence behind it for reducing recurrence in specific tumors. The decision to use adjuvant therapy, and which regimen to choose, should rest on tumor type, stage, molecular subtype, and overall condition. It should not rest on a subjective judgment about “constitution.” A successful surgery is not a reason to skip adjuvant therapy. Completing adjuvant therapy is not proof of “tumor constitution.”
Third, support the material basis of immune function instead of chasing abstract “regulation.” Strip the vagueness from “strengthen the constitution” and what remains is concrete: adequate protein and micronutrient intake, regular physical activity within medical limits, active management of treatment-related immunosuppression such as steroid use and myelosuppression, and mental health support that protects treatment adherence. These measures do not map to a single “anti-cancer mechanism.” They are the conditions the immune system needs to work. Postoperative rehabilitation resources are more likely to produce marginal benefit when spent on these measurable items than on “constitution regulation” that cannot be defined or verified.
Fourth, if DC vaccines are considered, put them inside a clinical trial. For specific patients with specific tumor types, such as the MGMT-methylated subgroup of glioblastoma, DC vaccines may be worth discussing in a well-designed trial. The discussion should start with whether the trial has concurrent controls, whether the primary endpoint is immunogenicity or survival, and what previous randomized trials in the same field found. It should not start with “Nobel Prize discovery” or “the FDA once approved a DC product.” A therapy approved for indication A is not automatically effective for indication B. A therapy with low-quality marginal evidence in tumor type C is not automatically promising for tumor type D.
Conclusion
Fear of postoperative recurrence persists partly because recurrence can feel like an unexplained, unpredictable, unmodifiable random event. That fear creates space for vague concepts like “tumor constitution” and overpromises like “DC vaccine breakthrough.” The evidence from the past five years points somewhere less dramatic and more useful. Recurrence is a process with molecular markers that can be tracked, biological mechanisms that can be understood, and clinical pathways that can be stratified.
A successful surgery deserves celebration. The celebration should not include lowering your guard and handing your judgment to a moving story. Responsible postoperative care starts by admitting the distance between “cleanly removed” and “cured.” Then it uses the most reliable tools available to measure that distance, monitor it, and act on the parts that can be acted on.
About the Creator
Jin
Writer of reamstories
https://reamstories.com/jin
Enjoyed the story? Support the Creator.
Subscribe for free to receive all their stories in your feed. You could also become a paid subscriber, letting them know you appreciate their work.
Comments
There are no comments for this story
Be the first to respond and start the conversation.